Table 1. Profile of the Participating Informal Caregiver. n = 10
X
Table 1. Profile of the Participating Informal Caregiver. n = 10
| Code |
Sex |
Age
(years)
|
Marital
status |
Situation
regarding
work |
Relationship to
the person being
cared for
|
| P1 |
Male |
47 |
Married |
Works for
someone else
|
Mother-in-law
|
| P2 |
Female |
56 |
Married |
Works for someone else, "Sick leave"
(temporary
incapacity for work)
|
Mother |
| P3 |
Female |
56 |
Married |
Works independently
|
Mother-in-law
|
| P4 |
Female |
57 |
Single |
Without salaried work
|
Mother |
| P5 |
Male |
73 |
Married |
Retired
|
Wife |
| P6 |
Female |
80 |
Married |
Retired
|
Spouse |
| P7 |
Female |
57 |
Married |
Works for someone else
|
Mother |
| P8 |
Female |
54 |
Married |
Works for someone else
|
Mother |
| P9 |
Female |
56 |
Widow |
Retired due to disability
|
Father and
Mother |
| P10 |
Female |
55 |
Married |
Works for someone else
|
Mother-in-law
|
P1 to P10 – Code
assigned to
each participant
To contextualize caregiving and the relationship between caregivers and care
recipients, half of the
participants provided care for a parent (50.00%), three cared for a mother-in-law (30.00%),
and two
cared for a spouse (20.00%). One participant provided care for two individuals. Most
participants
had siblings, except for P2, P6, and P7. In some cases, participants reported that their
siblings
had emigrated (P4 and P9). In 90.00% of cases, the care recipient lived in the same
household as the
caregiver, except for P3. In this case, the care recipient had temporarily moved into the
caregiver’s
home after becoming widowed, although they had previously lived as neighbors. Care was
provided
exclusively by 60.00% of participants (P2, P3, P4, P5, P6, and P9), whereas in 40.00% of
cases (P1,
P7, P8,
and P10), caregiving responsibilities were shared with spouses, siblings, or other
significant
individuals.
The need for informal caregiving emerged following acute conditions in 40.00%
of
cases, while most
situations resulted from chronic illnesses (60.00%). Across cases, participants reported
increasing
levels
of dependency and growing care demands over time. Regarding caregiving duration, four
participants
had been providing care for more than 10 years (P4, P6, P7, and P8). The remaining
participants had
been providing care for less than 10 years, including one participant for less than one year
(P2)
and
another for less than five years (P3).
In terms of time dedicated to caregiving, half of the participants devoted
all their
time to informal
caregiving (P2, P4, P5, P6, and P9), with one participant stating, “This is my job, 24 hours
a day”
(P9). Other participants provided care at more specific times of the day, such as in the
morning, at
lunchtime, and/or at night. Participants P1 and P10 provided care during the morning and
evening,
complementing formal support provided by a day care center.
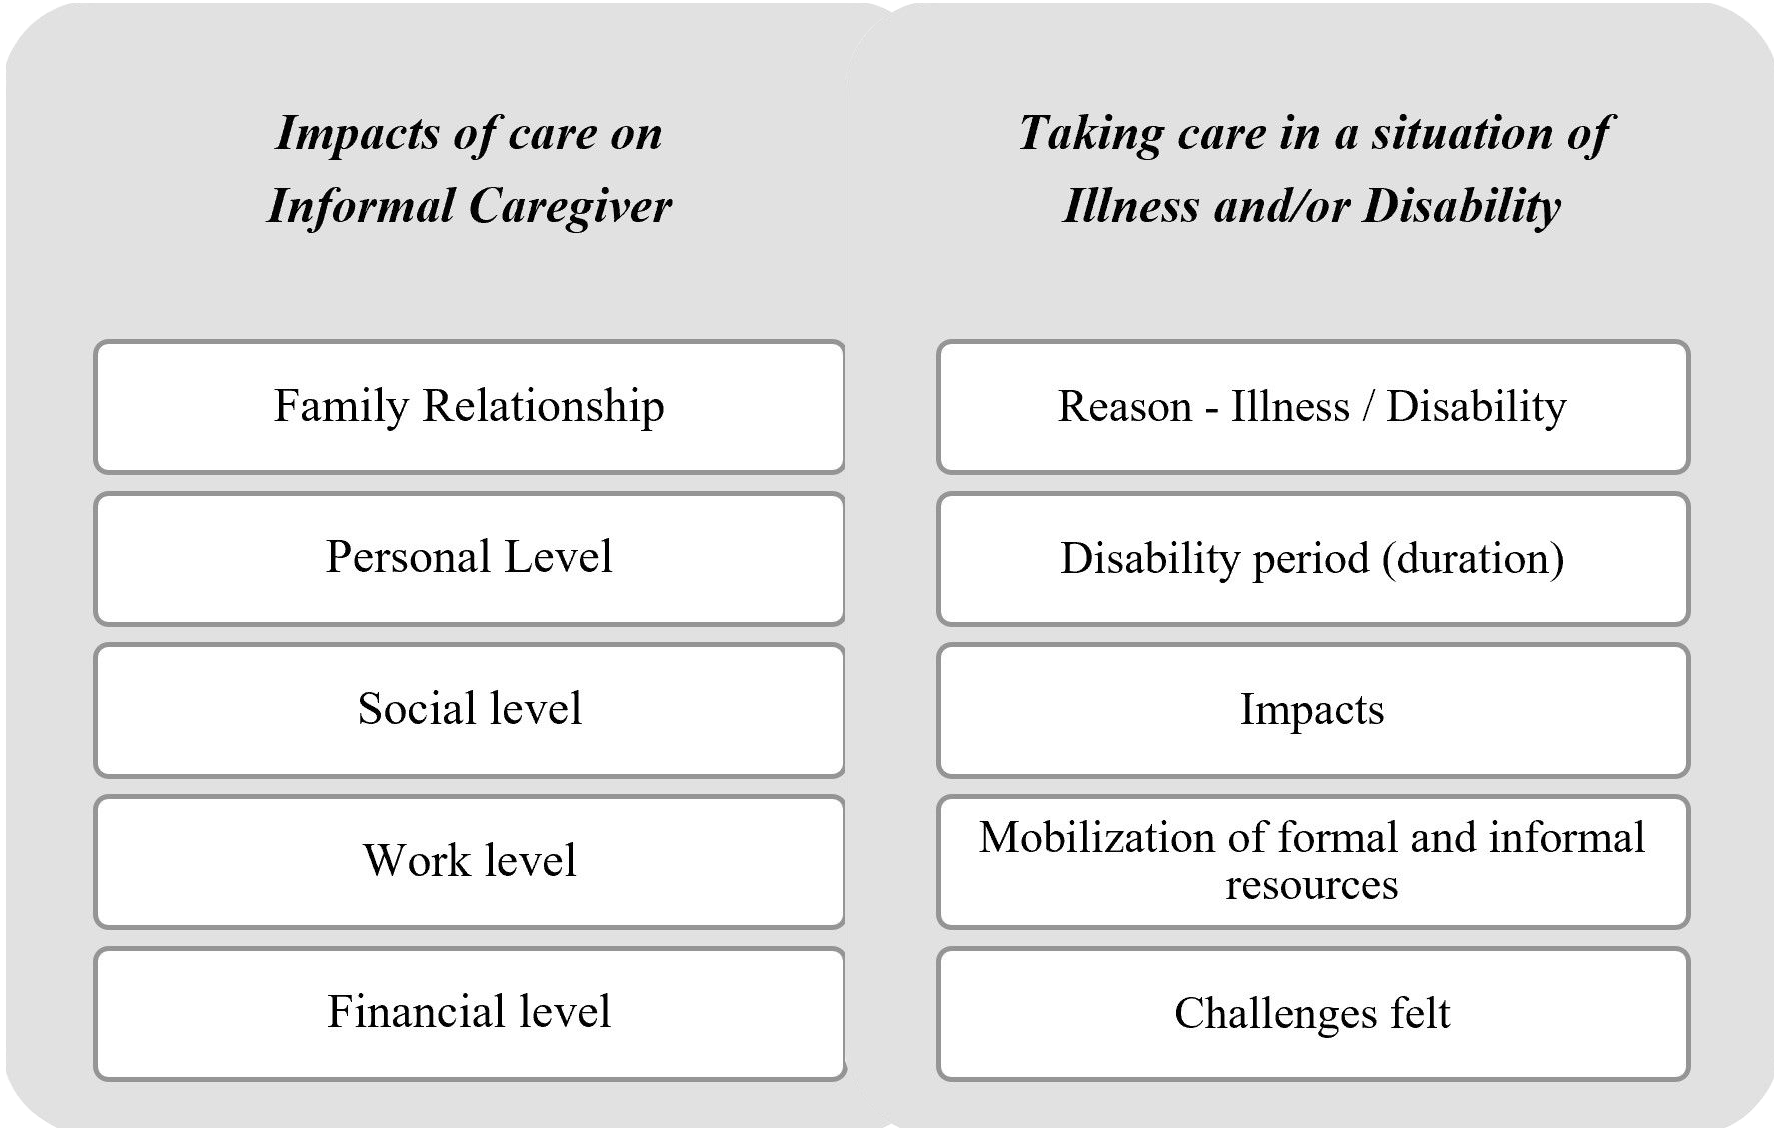
The results presented in this article focus on two categories: “Impacts of
caregiving on the informal
caregiver” and “Caregiving in situations of illness and/or disability.”
The category “Impacts of caregiving on the informal caregiver”
highlights
consequences at the
family, personal, social, occupational, and financial levels Table 2.
Table 2. Multidimensional impacts on the informal caregiver. n = 10
X
Table 2. Multidimensional impacts on the informal caregiver. n = 10
Subcategory
Impact / Unit of registration
|
% (n) |
|
At the Family Level
|
|
|
Family Dynamics
|
20.00 (2)
|
|
Family Relationships
|
20.00 (2)
|
|
No impact
|
50.00 (5)
|
|
Others
|
10.00 (1)
|
|
Difficulty managing routines and sleeping through the
night
|
20.00 (2)
|
|
On a personal level*
|
|
|
Restriction of autonomy to leave home or perform
activities
|
70.00 (7)
|
|
Wear and tear or fatigue
|
60.00 (6)
|
|
Fear of possible recurrence of the disease
|
10.00 (1)
|
|
At a social level
|
|
|
Restriction of freedom
|
80.00 (8)
|
|
No impact
|
20.00 (2)
|
|
At the Workplace level
|
|
|
Reconciling work and caregiving (with adaptations)
|
50.00 (5)
|
|
Dismissal
|
10.00 (1)
|
|
No impact
|
40.00 (4)
|
|
At the financial level
|
|
|
Increased expenses
|
50.00 (5)
|
|
Dependents cover expenses
|
20.00 (2)
|
|
No impact
|
20.00 (2)
|
|
Others
|
10.00 (1)
|
Note: *The variable allowed multiple responses. Therefore, the
multiple
responses for each variable justify the total percentage
of responses being greater than 100%
When asked about family-level impacts, half of the caregivers reported no
significant
effects. However,
regarding family dynamics, participants P1 and P7 indicated that caregiving had affected
family
relationships:
“The only issue that perhaps stirred things up a bit is with the routines. Where are
we
going to take them,
home, where are you going to pick them up from the day center, that dynamic until
it's
settled (...), until
they're established, it also affects our own routine a bit, there's a slightly
different
dynamic, it involves
many people, availability. It's one of the small challenges” (P1)
.
"I loved my grandchildren very much, I was always playing with them, and that's over
now."
(P7 about her mother who has been bedridden for 15 years).
Strained family relationships were reported by participants P3 and P4,
revealing that
the lack of
involvement of other family members in caregiving negatively affected family dynamics.
“The only support I asked for was that they come by, talk to her, 'you see?' Ask
questions,
because if
they
did that, by doing so, they would realize the progression of the disease, which was
what I
fought so
hard
against, that it was getting worse” (P3)
.
“Of course we have problems with each other, because there are always things to do
and it’s
dealt with.
Since I handle everything myself, it’s a bit complicated” (P4).
Personal-level impacts were the most frequently reported across interviews.
Six caregivers described personal impacts related to fatigue and burnout:
"It's just that whoever is
taking care
of someone like that, I think we get sick faster than the person
themselves.", "And sometimes I say, may God never make me go through something like
that
again,
because having to take care of someone like that is very painful" (P3).
“It’s a permanent, psychological exhaustion that then transforms into physical
exhaustion,
every day,
every day, every day, every day, every day, every day” (P9).
“If I went back home, I couldn’t take another month like this (…) It wasn’t
possible, I
couldn’t take it
like
this anymore, because psychologically, I couldn’t take it anymore” (P10).
Two participants indicated difficulty managing routines and difficulty sleeping at
night:
"Super complicated phase where she didn’t
sleep a
single night, she spent the night calling, calling all
the
children, and I basically spent the night here on the sofa. I wouldn’t wish this on
anyone,
on anyone at
all” (P10).
Finally, participant P1 expressed fear of relapsing into the condition that led to the
addiction,
stating:
“In the early years, I felt, at least I, and
she [my
wife] also, some apprehension about the possible
recurrence [of a stroke]” (P1).
Regarding social impacts, participants P2 and P9 did not report significant
effects
in this domain. The
remaining caregivers (80.00%) reported social impacts, as well as strategies used to cope
with
related
challenges. Restrictions on freedom and autonomy were reported by eight participants,
particularly
in
relation to leaving home and engaging in professional, leisure, or other daily
activities.
“Restrictions, constraints, limitations,
because
the simple fact that on a weekday, for example, we have
the freedom to not have dinner at home today, to have dinner out, during that period
of care
we cannot
do that. We have that schedule to follow, we must take care, yes” (P1).
“Sometimes we have activities that I belong to the community, and sometimes I can’t
make it
on Saturday
mornings” (P7).
"That's how it is, we're more stuck at home" (P8).
“Of course, it takes away my autonomy. I’m more tied to her, I can’t go out,
sometimes, a
person is
afraid
she’ll do something stupid because it’s not the first time, she’s threatened
(crying) (...)
even
downstairs
when I go out, I must leave her a written note, I went to get bread, I went over
there. And
even then,
sometimes, with that right in front of my eyes, it’s a problem. It raises problems
in
everything” (P5).
“I’m not going on vacation, I can’t, I have these tasks, we have these parts where
we give
up everything
to always be there every day, either one or the other [sister].” (P8).
“We knew that during the month she was here you weren’t doing much, right? Like
going
downstairs for
coffee. Someone had to stay with her like that” (P10).
Several strategies were described by caregivers to cope with these
limitations,
including postponing
scheduled events (P1), having one caregiver forgo social or professional commitments to
remain with
the care recipient (P1, P3, P7, and P10), and leaving the care recipient alone for short
periods (P5
and
P6), as illustrated in the following statements:
“One day perhaps I would still be able
to leave
her here one day, perhaps, but no more” (P5).
Other strategies mentioned include requesting someone to supervise the
dependent
person (P3, P4).
and the use of video surveillance cameras (P1, P4):
“I recently bought a video camera,
which I use
infrequently, because there isn’t much money to go out
to dinner with friends or anything like that, and I wear an earpiece and listen to
my
mother. I watch or
listen to see how she is doing, but it’s a rare occurrence” (P4).
Regarding occupational impacts, some caregivers reported that caregiving had
little
or no effect on
their professional lives, either because they were already on sick leave, retired, or
receiving
disability
retirement benefits (P2, P5, P6, and P9).
Half of the caregivers reported being able to reconcile paid employment with
informal caregiving
responsibilities, either due to flexible work schedules (P3 and P7) or through various
adaptations.
These adaptations included advance planning of professional activities (P1), reduced working
hours,
changing from rotating to fixed shifts (P8), and requesting shift changes with colleagues
(P10). One
caregiver reported needing to leave work after her mother underwent surgery (P4).
Regarding the financial impacts, half of the caregivers report increased
expenses, of
which P1 and P2
indicate that the family can afford them:
“That’s how it is, there are always
expenses,
although we usually say that the rice that feeds two,
feeds
three (...)”, “indirectly there were quite a few more expenses, but nothing
exceptional that
we couldn’t
handle” (P1).
“I had more expenses because, look, the chair was borrowed, but I had to get her a
walker
and buy
diapers. But thank God” (P2).
Some caregivers report that the dependents themselves bear the expenses
related to
their care (P7
and P9), as one participant mentions:
“No, it doesn’t affect me at all
because my
parents are financially independent. For now” (P9).
Other participants reported no longer experiencing financial difficulties
(P3 and
P10). In contrast, P8
stated that although reduced working hours resulted in lower income, overall expenses were
also
reduced due to the decision not to use formal care services.
The category “Caregiving in situations of illness or
disability”
encompasses data related to the
caregiving process when caregivers themselves experienced illness or disability. This
category is
divided into the following subcategories: (1) caregiver illness and/or disability; (2)
implications
for
caregiving; (3) mobilization of formal and informal resources; (4) challenges faced; (5)
caregivers’
current health status; and (6) perceptions regarding future caregiving.
Regarding the illness or disability experienced by caregivers,
hospital-based
treatments and surgical
procedures were the most frequently reported situations. In most cases, the period of
incapacity or
temporary unavailability lasted several weeks or months.
In the case of P4, despite physical limitations following surgery, the
participant
continued to provide
care immediately after the procedure. Several implications for caregiving were identified,
including
the need for rest, physical distance between the caregiver and the care recipient, and
difficulties
in
performing caregiving tasks Table 3.
Table 3. Caregiver Illness and/or Disability, Period of Unavailability, and
Implications
for
Caregiving. n = 10
X
Table 3. Caregiver Illness and/or Disability, Period of Unavailability,
and
Implications for
Caregiving. n = 10
|
Code
|
Caregiver's
illness and/ or
disability
|
Period of
unavailability
(duration)
|
Implications |
|
P1
|
Hernia
|
3-4 months of recovery.
|
The caregiver couldn't exert himself;
he needed rest. "At
that moment, he didn't have
the availability to care
for
her,
to hold Dona A's hand and take her here or there,
I
don't
know, help her down a step or get into the car."
|
|
P2
|
Breast
Cancer
|
Approximately 1 year of
treatments.
|
When she undergoes oncology hospital treatments, she
becomes unavailable; she mentions being
tired. "Yes,
tired,
I was tired, but I treated her anyway."
|
|
P3
|
Covid-19
|
Unavailable for 1 week.
|
Caregiver is unavailable to provide daily care.
|
|
P4
|
Sebaceous cyst surgery
|
Immediately after surgery.
|
The caregiver continued to provide care despite being
prohibited
from exerting herself;
she reports feeling tired.
“A person really needs to rest, which I didn’t do. I
felt more
tired,
I had headaches, I was sleepier, but I did
the work
anyway. I forced myself to do it.”
|
|
P5
|
Hospital emergency due to loss of consciousness.
Prostate
cancer and heart problems.
|
20 hours in emergency rooms
and during cancer treatments.
|
During visits to the emergency room, she was unable to
provide care, and when she underwent
oncological
hospital
treatments, her availability also decreased
significantly.
|
|
P6
|
Complex
surgery. Caregiver
with cancer problems
|
Two days a week with hospital
treatments over several months.
|
When someone undergoes hospital treatment, they are no
longer able to provide informal care.
"In 2011, I
spent more
time in the hospital than almost at home."
|
|
P7
|
Surgery
for a brain tumor
|
Hospitalization for 15 days and
recovery at home.
|
The caregiver mentions the need for rest and notes that
she
experienced dizziness and sometimes
couldn't see
bright
light, which made it difficult to perform caregiving
tasks.
|
|
P8
|
Hand
surgery
|
Sick leave for 1 month, but
started taking care of things
after 15 days.
|
The caregiver mentions the need for rest and increased
difficulties in providing care during the first
few
weeks
after surgery.
|
|
P9
|
Breast
surgery. (previously:
other surgeries and Covid-19)
|
1 week of hospital stay.
|
The caregiver mentions the need for rest and the
inability
to exert oneself during the initial recovery
phase
at home.
|
|
P10
|
Bowel
surgery
|
Recovery over several weeks.
|
The caregiver mentions the need for rest. Due to the
rotation of caregivers, after two months the
dependent
returned home. When questioned about the implications,
she replies: "I think she had them all."
|
Regarding the mobilization of formal and informal resources in response to the caregiver’s
illness
or disability, 90.00% of participants reported strengthening support from their existing
informal
network (except for P4). New requests for support were also identified within the informal
network (P3,
P6, and P7) and the formal network (P2)
Table 4.
Regarding caregiving support networks, all participants mentioned at least one person who
provides
support in caregiving or someone they could rely on if needed, whether through formal or
informal
support. For 60.00% of the sample, the caregiving support network was mixed. It was exclusively
informal in 30.00% of cases and exclusively formal in 10.00%. The formal support network
mobilized
included home support services (P3, P7), day centers (P1, P10), formal in-home caregivers (P3,
P4),
physiotherapy services (P6, P9), and parish council services for activities for older adults
(P9).
Table 4. Mobilization of Formal and Informal Support Resources During the
Caregiver's
Illness
or Disability Period. n = 10
X
Table 4. Mobilization of Formal and Informal Support
Resources
During the
Caregiver's Illness or Disability Period. n = 10
|
Subcategory
|
Appealed % (n)
|
Did not appeal %
(n)
|
Strengthening the support of the existing informal network
|
90.00 (9)
|
10.00 (1)
|
New requests for support on the informal network
|
30.00 (3)
|
70.00 (7)
|
New support requests on the formal network
|
10.00 (1)
|
90.00 (9)
|
Table 5 details the mobilization of formal and informal support, including
excerpts
from interviews
illustrating how participants managed the impact of the caregiver’s illness on the caregiving
process for the dependent person. Most participants (80.00%) reported barriers to accessing
formal
support services. These barriers included high financial costs (P2, P6, P8), difficulties
related to
daily
logistics, a preference for receiving care at home from an informal caregiver (P4, P7, P9), and
concerns
about the perceived quality of services (P5, P8, P9).
Table 5. Mobilization of Formal and Informal Resources in the context of Illness
or
Disability of
the Informal Caregiver. n = 10
X
Table 5. Mobilization of Formal and Informal Resources in the context of
Illness
or Disability of
the Informal Caregiver. n = 10
|
Code
|
Strengthening the
Mobilization of formal and informal resources
|
|
P1
|
Strengthening the informal support network.
The participant stated that he did not feel the need to
seek
additional support, although his wife experienced an
increased
caregiving burden. As he explained. “In the weeks
when she
wasn’t
there, I could rest, and in the weeks when she was,
I
burdened
Mrs. C a little more; she was the one who did
everything”. The
participant also mentioned the temporary availability of
support from neighbors.
|
|
P2
|
Strengthening the informal support network and a new
request for
support from the formal network.
The participant reported increased support from her
husband and
cousin. She also mentioned that, when she was unable to
stay with her mother, she asked a neighbor to care for
her
through a paid service.
Home care services were suggested by the hospital;
however, the
caregiver declined this option, explaining: “They
said they
could only come once a week to clean the house,
cook, and
take
care of her. Once a week wasn’t going to solve
anything, so
I
gave up”.
|
|
P3
|
Strengthening the informal support network and a new
request for
support within the informal network.
The caregiver temporarily stopped providing care. During
the
first few days, caregiving responsibilities were assumed
by her
husband, followed by a brother-in-law. However, due to
his
limited availability because of work commitments, the
family
decided to leave the dependent person in the care of the
mother-in-law of one of the brothers-in-law.
As the participant explained, “For me, COVID was the
opportunity
I had to finally step away, allowing them to stay
with her
and realize the condition she was in”.
|
|
P4
|
There was no strengthening of the support network or any
new
request for formal or informal support.
|
|
P5
|
Strengthening the informal support network.
During the caregiver’s treatment, he stayed with his
wife in a
residential care facility. He reported having requested
assistance
from staff members while he was in the emergency room.
During
that emergency episode, his daughter stayed with her
parents for a few days to provide additional support.
As he explained, “Yes, when I was in the emergency
room for 20
hours, I asked the staff at the residence to keep an
eye on her
and
help her become familiar with the room, because even
after 8,
10, or 15 days there, she still wasn’t fully
comfortable with
the door.”
|
|
P6
|
Strengthening the informal support network and a new
request for
informal support.
During the caregiver’s hospital treatment, the couple’s
daughter
assumed caregiving responsibilities, and the dependent
person stayed overnight at her home. When the daughter
was
unavailable, another woman stayed overnight at the
couple’s
home to provide care for the dependent person.
As the participant explained, “Sometimes my daughter
would come,
especially when she was on vacation. Otherwise, a
woman
from Póvoa de Sobrinhos would come and stay
overnight at my
house.”
|
|
P7
|
Strengthening the informal support network and a new
request for
informal support.
During the recovery period, due to the caregiver’s
temporary
incapacity, her sister assumed caregiving
responsibilities. At
times, the sister also sought assistance from a cousin
to help
with caregiving.
|
|
P8
|
Strengthening the informal support network.
During her recovery, her sister provided care.
|
|
P9
|
Strengthening the informal support network.
During the surgery and recovery period, the caregiver
was no
longer able to provide care and required care herself.
Her
sister,
daughter, and mother provided support to both the
caregiver and
the dependent person.
As the participant explained, “At first, my daughter
was here;
she even washed my clothes and shirts, visited me,
and brought
me everything I needed. Then she left, and my sister
came. If I
hadn’t had them, well, I don’t know (laughs).”
|
|
P10.
|
Strengthening the informal support network.
During her recovery, the caregiver received increased
support
from family members and neighbors in providing care for
her
mother-in-law.
|
Regarding the challenges experienced, 50.00% of participants reported
difficulties related to the
caregiver’s own recovery, while 30.00% identified the impossibility of leaving the dependent
person
alone. Participants also reported feelings of isolation during this process, the burden
associated with
caregiving, and challenges related to caregiver support services.
“There were times when I felt somewhat
unsupported by the social services, that is, while, yes ma'am, I
was at the day center, but in fact, when you are limited in your functions it seems
like there's no one else,
let's say, you need a little help, there's no one” (P1).
“I think all caregivers should have a psychologist, that’s what I think, so they can
talk about things
they don’t talk about with anyone else, because people don’t even understand,
because they don’t go
through the same thing, they don’t know what it’s like to be caregivers”
(P4).
"I think they were very big challenges, psychological ones, I had a lot of patience,
it was very complicated"
(P10).
Regarding the caregiver’s current health status, half of the participants
reported feeling well (P3, P4,
P6, P8, and P10). The remaining participants reported health problems and limitations
related to
their illness or recovery process. Regarding perceptions of the future of caregiving, most
participants
anticipated a worsening of the dependency situation (40.00%). Others expressed concern about
the
future (20.00%), while some believed they would continue providing care as long as they
remained
healthy (30.00%). In contrast, P4 and P6 reported not thinking about the future. In the case
of P10,
the family member receiving care had died (10.00%).
“If I’m healthy and ready, I’ll see it
through to the end. If not, something must be sorted out later, right?”
(P2).
“I don’t know what’s going to happen, or when, I can’t be thinking about the future,
at this moment
thinking about how I’m going to take care of things from now on, what’s going to
happen, because I
don’t know. Challenges arise and we try to solve them” (P4).
Discussion
The profile of the informal caregivers participating in this study was
predominantly female, with a mean
age of approximately 60 years. Most were married and employed. All participants provided
care to
family members (mother, father, mother-in-law, or spouse) and lived with the care recipient.
This profile
is consistent with that identified in studies conducted in Portugal11,13,
23,24.
The results revealed that caregiving had multidimensional impacts on the
lives of informal caregivers,
affecting family, personal, social, occupational, and financial domains. At the family
level, half of the
participants reported no significant impact. When impacts were identified, these were
related to family
routines and dynamics, as well as relationships between family members, with increased
conflict
associated with caregiving responsibilities. At the personal level, all caregivers reported
some type of
impact, including restricted autonomy to leave home or engage in personal activities,
burnout, fatigue,
difficulties managing daily routines, and sleep disturbances.
At the social level, caregivers reported restrictions on their own freedom
and that of their family
members, particularly regarding leisure activities and vacations. At the occupational level,
employed
caregivers reported adjusting balance paid work and caregiving responsibilities, including
greater
flexibility, reduced working hours, reduced professional activities, or self-employment. One
participant
left her job to care for her mother because she was unable to reconcile caregiving with her
professional
responsibilities, while another was temporarily unable to work. Finally, in financial terms,
half of the
participants reported increased household expenses associated with providing informal care.
The literature also highlights the multidimensional nature of these impacts.
Families experience
changes in their routines when they begin providing informal care13. Family
conflicts have
also been
reported, particularly among siblings7. In the personal domain, several impacts
on
caregivers have
been identified7,18,19. Notably, the loss of freedom to leave
home and engage in personal
activities
may contribute to social isolation15. Being an informal caregiver has also
been associated
with reduced
leisure time, reflecting the burden experienced by caregivers25,26.
Balancing work and caregiving responsibilities presents significant
challenges and may lead to job
abandonment, particularly when caregiving is prolonged27,28. In line with the present
findings, a study
conducted in Portugal found that 52.50% of caregivers were active in the labor market and
reported
no significant impact on their working lives. However, some participants reported
difficulties related
to justifying absences and sick leave, reduced working hours, income-related problems,
challenges in
balancing professional and family responsibilities, burnout11. Support from
social
protection systems
for informal caregivers remains limited, even after the formal recognition of caregiver
status in
Portugal, particularly when caregiving is associated with increased financial
burden27.
This study also examined informal caregiving in situations where caregivers
experienced illness or
disability, focusing on the impacts and challenges faced, the formal and informal support
mobilized,
and future perspectives regarding caregiving.
The illness of the informal caregiver represents a significant challenge,
with clear repercussions
for the caregiving process. Participants highlighted issues such as physical distance
between the
caregiver and the care recipient, inability or difficulty in performing caregiving tasks,
fatigue, and
an increased need for rest. Half of the caregivers identified their own recovery process as
a major
challenge, followed by difficulties related to not being able to leave the care recipient
alone, the
burden associated with caregiving, challenges in accessing support services, and feelings of
isolation
throughout the caregiving process. These impacts and challenges reveal the limited
availability of
resources to help caregivers cope with the accidental crisis caused by illness, highlighting
the need
for greater support. In this context, the mobilization of both formal and informal resources
becomes
essential. In response to caregiver illness, 90.00% of participants strengthened their
informal support
network, 30.00% sought additional resources within the informal network, and 10.00% sought
support from the formal network. A clear preference for informal social support was evident.
The literature suggests that caregivers are likely to experience high levels
of stress when they lack
the internal or external resources necessary to cope with crises such as illness,
particularly when
pre-existing health problems are present29. The importance of mobilizing
additional
resources,
including support from other caregivers, has also been highlighted as a strategy to mitigate
some of
the impacts and challenges identified in this study29.
When asked about their perceptions of the future of caregiving for their
family members, participants
highlighted the anticipated worsening of the dependency situation, followed by the belief
that
caregiving would continue as long as the caregiver remained healthy. Concerns about the
future, as
well as avoidance of thinking about it, were also reported.
Analysis of participants’ narratives revealed feelings of hope, uncertainty,
and sadness, findings that
are also consistent with those reported by Guadalupe et al.27. The future may present
additional
challenges for informal caregiving, both due to the worsening health condition of the
dependent
family member and the deterioration of the caregiver’s own health. Evidence suggests that
caregivers are themselves at risk of illness, and that this risk may be reduced through
stronger formal
support systems for caregiving30.
This study has limitations that should be acknowledged. First, difficulties were encountered
in sample
recruitment due to the specificity of the target population, despite the use of
non-probabilistic
sampling techniques. In addition, some analytical categories would benefit from greater
saturation, particularly those related to occupational and personal impacts. The study
adopted a homogeneity
criterion regarding caregivers’ experiences of temporary disability and clinical inability
to provide
care, excluding situations involving mental health conditions. Future research should
include a
broader range of illness and disability situations among caregivers, with particular
attention to the
implications of the duration of incapacity for caregiving and the degree of temporary
disability
experienced by the caregiver. Studies with larger samples and quantitative, correlational
designs are
recommended to explore potential associations between variables.
Conclusions
The findings highlight that informal caregiving has multidimensional impacts
on both caregivers
and their families. The personal, social, and occupational impacts are particularly
significant. At
the personal and social levels, notable challenges include restrictions on autonomy to leave
home,
reduced leisure time, and experiences of fatigue and burnout. At the occupational level,
employed
participants reported being able to balance caregiving and work through adjustments to their
professional activities and work schedules, although in some cases informal caregiving led
to
temporary or permanent withdrawal from employment.
Caregiver illness and/or disability further intensifies the impacts and
challenges associated with
caregiving, revealing an increased need for social support. The study also identified
barriers to
accessing formal social services and to combining formal and informal sources of support.
Given the barriers to accessing formal support, greater monitoring and
follow-up by primary
health
care and community social services are essential, particularly in situations involving
caregiver
illness,
as caregivers often feel isolated and unsupported throughout the caregiving process. Social
Work
play a crucial role in supporting this population by safeguarding rights and well-being,
strengthening
social support networks, and mitigating the adverse impacts of informal caregiving.
What happens when the informal caregiver becomes ill? This fundamental
question motivated the
present study. Given the scarcity of studies addressing this specific situation in
scientific
literature,
this research represents a relevant contribution to the existing body of knowledge and
provides
a
solid foundation for future studies in this field.
Informal caregivers play a vital social role. However, they are also
vulnerable to illness or
disability
that may compromise their ability to provide care. When faced with such circumstances, where
can
they turn and on whom can they rely? The findings clearly indicate that caregivers primarily
rely
on their informal social support networks, particularly family ties, highlighting the
family-centered
nature of caregiving in Portugal8.
Participants’ narratives also suggest that maintaining informal caregiving
remains a central
priority, if
caregivers are physically able to assume caregiving responsibilities and remain in good
health.
This study highlights the need for integrated interventions combining health
care and
communitybased
social care to ensure effective support for informal caregivers. Strengthening public
policies
aimed at supporting caregivers is essential. In particular, the implementation of integrated
support
programs for informal caregivers is recommended, with special attention to caregivers at
risk of
illness
or already experiencing illness. Additionally, community-based social care services for
dependent
populations should be re-evaluated and made more flexible to better respond to caregiving
needs.
Conflicts of Interest: The authors declare that they have no conflicts of
interest.
Funding: This research received no external funding.
Author contributions: ICD: Conceptualization; Data Curation;
Investigation; Methodology; Resources;
Validation; Visualization; Writing – Original Draft Preparation. SG: Conceptualization; Data
Curation;
Formal Analysis; Investigation; Methodology; Supervision; Validation; Visualization; Writing
– Original
Draft Preparation; riting – Review & Editing.
References
-
Eurocarers.
The gender dimension of informal care. [Internet] 2021 [cited 2025 july 1].
Available
from:
https://eurocarers.org/publications/the-gender-dimension-of-informal-care/
-
Entidade Reguladora da Saúde-ERS.
Acesso, qualidade e concorrência nos cuidados
continuados e paliativos. Entidade Reguladora da Saúde, Portugal. 2015. Consulta:
julho 16, 2025.
Disponível em:
https://www.ers.pt/media/o0mdazvz/file-55.pdf
-
Fundação Francisco Manuel Dos Santos- PORDATA. 2025.
Consulta: Maio 20, 2025. Disponível
em:https://www.pordata.pt/
-
Guadalupe S, Cardoso J.
As redes de suporte social informal como fontes de provisão social
em Portugal: o caso da população idosa. Sociedade e Estado. 2018;
33(1):213–48.
https://doi.org/10.1590/s0102-699220183301009
-
Moreira MJG.
Como envelhecem os portugueses: Envelhecimento, saúde, idadismo. Fundação Francisco
Manuel dos Santos. 2020.
http://hdl.handle.net/10400.11/7409
-
Serra I, Gemito ML.
Cuidadores informais: Quem quer ou quem pode? In: Mendes, F; Gemito,
L; Cruz, D. & Lopes, M. (coord.) Enfermagem Contemporânea: Dez Temas, Dez Debates.
Nº 1.
Colecção E-books. Oficinas Temáticas. pp. 132-149. ISBN: 978-989-20-4162-9.
http://hdl.handle.net/10174/10411
-
Pimentel L. Filho és, Pai serás... Cuidar de
Pessoas Idosas em Contexto Familiar. Coisas de Ler Edições. 2013.
-
Guadalupe S, Vicente HT.
Família e outras redes de suporte social na população idosa. In:
Santos CC, Teixeira M, editors. Intervenções e mediações com idosos. Imprensa da
Universidade de Coimbra. 2021, p. 63-97.
-
Araújo M, Soeiro J.
Trabalho, reconhecimento e justiça social: O caso dos cuidados informais
em Portugal. e-cadernos CES. 2021;15(35).
https://doi.org/10.4000/eces.6164
-
Movimento Cuidar dos Cuidadores Informais.
Estudo sobre a perceção dos portugueses
sobre cuidadores informais. [Infographic] 2021 [Cited 2025 Maio 20]. Disponível em:
https://movimentocuidadoresinformais.pt/wp-content/uploads/2021/04/cuidadores-informais_infografia_A4.pdf
-
Carvalho MI.
Estudo sobre o Perfil do Cuidador Familiar/Informal da Pessoa Sénior em
Portugal.
ISCSP-ULisboa, CAPP/ ISCSP-ULisboa, Fundação Aga Khan, Johnson & Johnson Foundation.
2022.
Consulta: Maio 20, 2025. Disponível em:
http://hdl.handle.net/10400.5/29181
-
Barbosa F, Voss G, Matos AD.
Health impact of providing informal care in Portugal. BMC Geriatrics.
2020;20.
https://doi.org/10.1186/s12877-020-01841-z
-
Movimento Cuidar dos Cuidadores Informais.
O que é ser Cuidador Informal em Portugal?
[Infographic] 2021 [Cited 2025 julho 16]. Disponível em:
https://movimentocuidadoresinformais.pt/wp-content/uploads/2021/04/cuidadores-informais_infografia_2021_A4.pdf
-
Organisation for Economic Co-operation and
Development.
Health at a glance 2017: OECD
indicators. OECD Publishing. [Internet] 2017 [cited 2025 May 18]. Available from:
https://doi.org/10.1787/health_glance-2017-en
-
Costa MIA.
Quem cuida de quem cuida? Estudo sobre o regime jurídico dos cuidadores
informais e pessoas dependentes em Portugal [Thesis Mestrado em Direitos Humanos]
Portugal,
Universidade do Minho; 2022. Disponível em:
https://hdl.handle.net/1822/84738
-
Sequeira C.
Cuidar de idosos com dependência física e mental. Lidel; 2010.
-
Guimarães AC, Freitas L, Costa SO, Brandão V.
Cuidar de Quem Cuida: Ferramentas de Avaliação
dos Cuidadores: Caring for Carers: Caregiver Assessment Tolls. Gazeta Médica.
2020;7(1).
-
Portugal S.
Dádiva, família e redes sociais. In: Portugal S, Martins PH, editors. Cidadania,
políticas públicas e redes sociais. Imprensa da Universidade de Coimbra. 2011, p.
39–
54. https://estudogeral.uc.pt/bitstream/10316/41478/1/%EF%BB%BFCidadania%2C%20pol%C3%ADticas%20p%C3%BAblicas%20e%20redes%20sociais.pdf
-
Figueiredo D.
Cuidados familiares ao idoso dependente. Climepsi Editores. 2007.
-
Hoffmann F, Rodrigues R. Informal carers: Who takes care of them?
Policy Brief 4/2010.
European Centre. [Internet] 2010 [cited 2025 may 18]. Available from:
https://www.euro.centre.org/downloads/detail/1256
-
Glaser BG, Strauss AL.
The discovery of grounded theory: strategies for qualitative research.
Chicago: Aldine Publishing Company; 1967.
-
Durão I, Guadalupe S.
“CareD”. Mendeley Data V1. 2025.
https://doi.org/10.17632/b93jp9pn22.1
-
Guerreiro CM, Gemito ML, Caldeira EV, Coelho AP, Moita
ER.
Sobrecarga e qualidade de
vida dos cuidadores informais de idosos dependentes. Revista Ibero-Americana de
Saúde e
Envelhecimento, 2022;8(2):225–39.
https://doi.org/10.24902/r.riase.2022.8(2).560.225-239
-
Sequeira C.
Difficulties, coping strategies, satisfaction and burden in informal Portuguese
caregivers. Journal of Clinical Nursing. 2013;22(3-4):491–500.
https://doi.org/10.1111/jocn.12108
-
Inouye K, Pedrazzani ES, Pavarini SCI.
Implicações da doença de Alzheimer na qualidade de
vida do cuidador: um estudo comparativo. Cadernos de Saúde Pública.
2010;26(5):891–9. https://doi.org/10.1590/S0102-311X2010000500011
-
White-Means SI, Chang CF.
Informal caregivers’ leisure time and stress. Journal of Family and
Economic Issues. 1994;15:117–36.
https://doi.org/10.1007/BF02353636
-
Guadalupe S, Costa É, Daniel F.
Sentimentos face ao futuro, necessidades percebidas e redes
de suporte social de cuidadores informais de pessoas adultas com deficiência.
Revista Portuguesa
de Investigação Comportamental e Social. 2016; 2(1):53–66. https://doi.org/10.7342/ismt.rpics.2016.2.1.27
-
Soeiro J, Araújo M, Figueiredo S.
Cuidar de quem cuida. Penguin Random House. 2020.
-
Roth DL, Fredman L, Haley WE.
Informal Caregiving and Its Impact on Health: A Reappraisal
from Population-Based Studies. The Gerontologist. 2015; 55(2):309–19. https://doi.org/10.1093/geront/gnu177
-
Grunfeld E, Glossop R, McDowell I, Danbrook C.
Caring for elderly people at home: the
consequences to caregivers. CMAJ: Canadian Medical Association journal =
journal de
l’Association
medicale canadienne. 1997;157(8):1101–5. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC1228268/