Author/year/
country/
|
Study objective |
Study design
|
Population |
Type of intervention |
Cataldo31
,
2001 USA
|
To highlight the importance of the role
of psychiatric nurses in the assessment
and treatment of tobacco use.
|
Quantitative
descriptive
|
Psychiatric
patients and
individuals
with substance
use disorders
|
- Pharmacological treatment to quit smoking.
- Individualized counseling to quit smoking.
- Education on the risks and benefits of quitting
smoking.
- Ongoing follow-up and emotional support for
patients.
|
WHO25
2008 Asia
|
Describe the management of health
problems in drug users.
|
Descriptive
|
Healthcare
professionals
|
- Medical treatment for infections and diseases
common
among drug users. Vaccination against hepatitis
and tetanus.
- Provision of clean needles and sterile injection
equipment.
- Education on the prevention of infectious
diseases.
|
Pengpid et
al.26
,
2013
South Africa
|
To evaluate the effectiveness of a
Screening and Brief Intervention- SBI
for
alcohol problems among university
students in South Africa.
|
Quantitative
study -
controlled trial
|
College
students
|
- Screening to identify problematic alcohol use.
- Brief intervention to discuss strategies for
reducing excessive
alcohol consumption.
- Information-Motivation-Behavioral Skills (IMB)
model.
|
Burr et al.30
,
2014
USA /
New Jersey
|
To describe the implementation of a
nurse-led health promotion and disease
prevention program in needle exchange
programs.
|
Quantitative
Descriptive
|
People who
inject drugs
|
- Provision of clean syringes and safe injection
equipment.
- Access to medical care and HIV/hepatitis
testing.
- Education on safe injection practices and
overdose
prevention.
|
Patestos
et
al.27
,
2014
USA
|
Analyzes the roles of school nurses
in preventing substance abuse among
school-aged children through a model
of continuous care.
|
Quantitative
descriptive
|
School-aged
children and
adolescents
|
- Early detection of substance abuse problems.
- Educational programs in schools on the risks of
drug use.
- Connecting students with counseling or treatment
services.
|
Gutierrez
et
al.24
,
2015
USA
|
To identify the current prevalence and
societal impact, as well as the etiology,
comorbid psychiatric disorders, and
treatment and prevention of drug and
alcohol use among adolescents.
|
Descriptive
study
|
Adolescents
|
- Education on the harmful effects of alcohol
and drug use.
- Behavioral and family therapies.
- Prevention of initiation of use through
informational talks.
|
Sharma
et
al.32
,
2017
Toronto
Canada
|
Involving people with
firsthand experience with drug use as
partners in the delivery of clinical care.
|
Quantitative
study
|
Adults and
adolescents
|
- Provision of sterile supplies (syringes) to drug
users.
- Treatment of drug-related infections.
|
Lintzeris
et
al.28
,
2020
Australia
|
Implement and evaluate a
NHT intervention targeting
individuals at high risk of opioid
overdose, specifically those with a
history of opioid use disorder and/or
injection drug use.
|
Mixed-methods
study
|
Adults and
adolescents
|
- Distribution of naloxone and training on its
use.
- Education on how to identify signs of overdose.
|
Mullennix et
al.34
,
2020
USA
|
Describe the implementation of a
clinical nurse specialist-led emergency
department overdose education and
naloxone distribution program.
|
Quantitative
study
|
Patients of all
ages who have
experienced
an opioid
overdose or
are at risk
of opioid
overdose
|
- • Naloxone distribution in the emergency
department.
- Training for patients and family members on
naloxone
administration.
- Screening of patients at risk of opioid
overdose.
- Education on the risks of overdose and opioid
use.
- Referral to opioid dependence treatment
services.
- Post-discharge follow-up to ensure access to
care and
treatment resources.
|
|
Clua-García35
,
2021
Spain
|
Understanding nursing care in
supervised consumption sites (SCSs)
and proposals for more effective
intervention.
|
Qualitative study
with an
ethnographic
approach
|
People in
vulnerable
situations
|
- Supervision and care in supervised consumption
sites.
- Connection to health services and treatment for
drug users.
|
Perera et al.33
,
2022
California
|
To describe the implementation of
a hospital-based intervention that
provides harm reduction education
and supplies to patients through an
addiction consultation team at an
urban safety-net hospital.
|
Quantitative
study
|
Adults
|
- Implementation of harm reduction programs in
hospitals.
.- Provision of medical care to people with
substance use
disorder.
|
Morales
Loyola29
,
2020-
2022
Cuernavaca
|
Promoting social skills through an
e-Health educational initiative with a
focus on reducing the risks and harms
of psychoactive substance use among
school-aged adolescents in the State of
Mexico.
|
Nonexperimental
study with prepost
intervention
measurement
using a mixedmethods
approach
|
Secondary
school
adolescents
|
- • Use of digital platforms for education on the
risks of
substance use.
- Prevention of problematic use among adolescents
through
accessible information.
- Education on the risks of substance use through
the use of
digital platforms.
|
HIV: Human Immunodeficiency Virus, NHT:
Take-home naloxone, SCSs: Supervised consumption sites
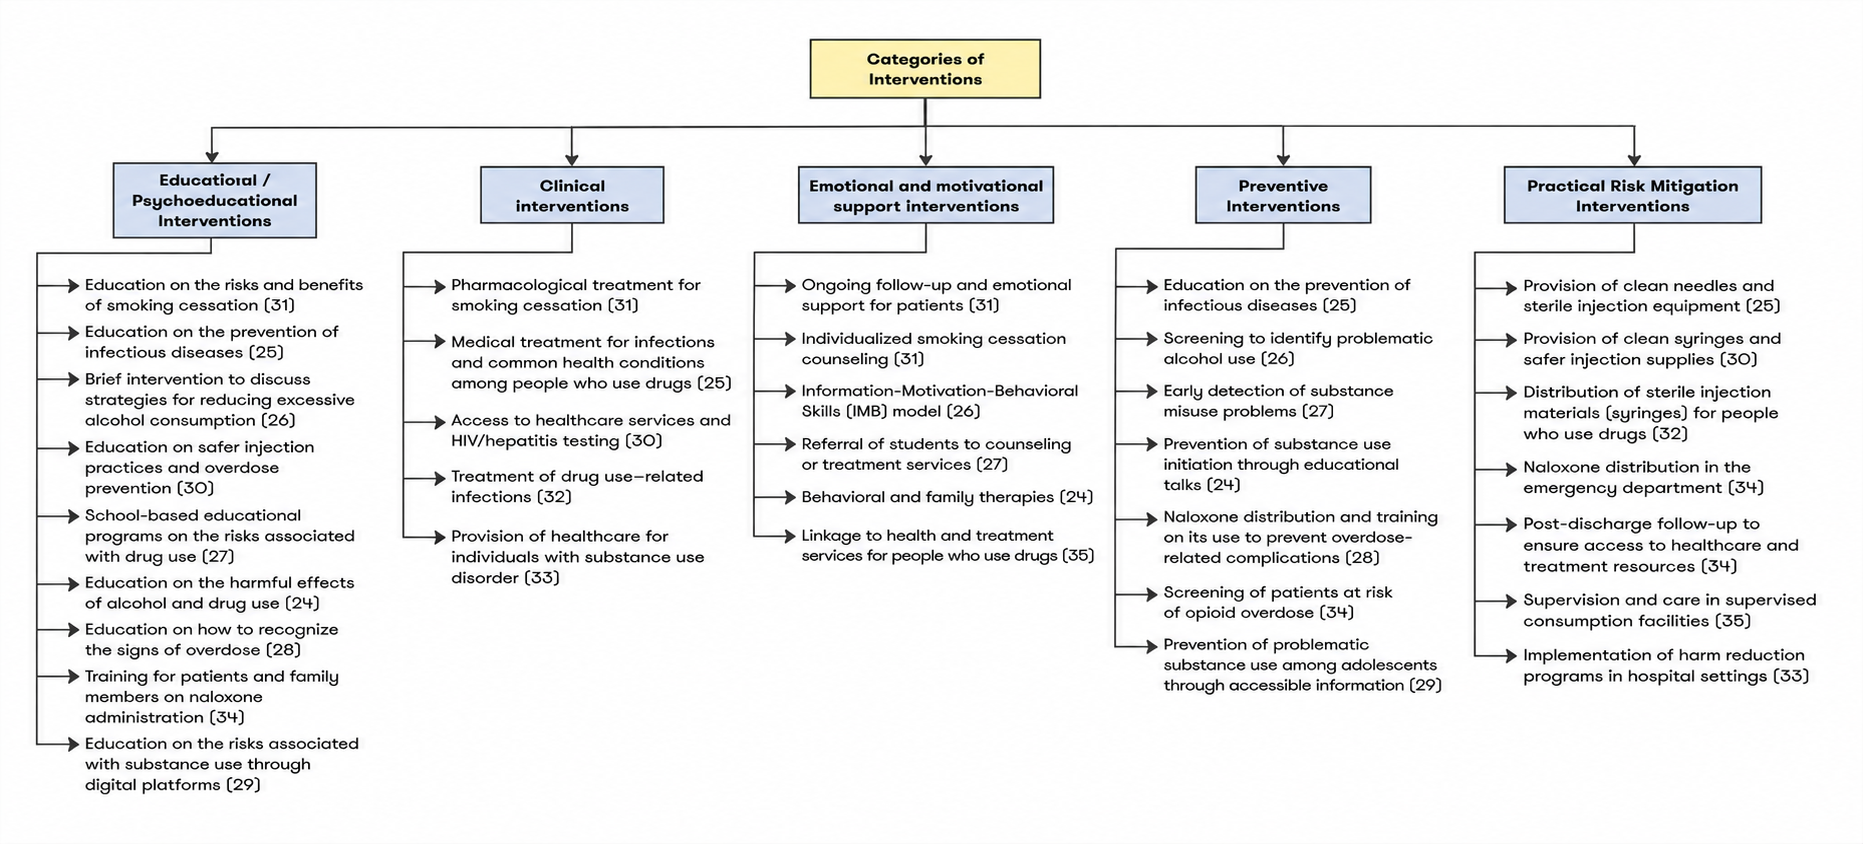
Figure 2. Conceptual map of nursing interventions organized by category
Categories created based on the authors’ reports and detailed in Supplementary Material22
Educational or psychoeducational interventions
The results show that educational interventions led by nursing professionals were the most
frequently
reported in the included studies. These strategies were primarily aimed at strengthening knowledge
about the risks associated with substance use, promoting self-care practices, and harm
reduction24.
Through educational programs in various settings, they aimed to raise awareness of the risks of
tobacco,
alcohol, and other drug use using the 5R model (relevance, risks, rewards, roadblocks, and
repetition),
seeking to increase patients’ motivation to quit25,26.
In schools, these interventions provided students with a comprehensive understanding of the harmful
effects of drugs, leading to a decrease in their use. Additionally, brief interventions were
conducted with
students at risk of substance use, informing them about the physical, psychological, and social
effects of
substance use and strengthening their willingness to adopt healthier behaviors27.
Other strategies included education on safe injection practices and overdose prevention, training
to recognize signs of overdose and the proper use of naloxone, which helped connect users with
community treatment and mental health services, strengthening comprehensive care and promoting
safer practices25,30.
Clinical Interventions
It was observed that clinical interventions provided by nursing professionals, such as smoking
cessation
treatment through counseling and pharmacological therapies, proved effective in reducing physical
and psychological dependence, increasing motivation to quit using31. Likewise, interventions aimed
at treating infections and communicable diseases in people who use drugs were described, including
sexually transmitted infections, skin lesions, and abscesses associated with injection drug use,
through
the use of antibiotics, antivirals, and procedures such as incision and drainage, when necessary,
along
with vaccination programs against Hepatitis B and tetanus.
Furthermore, the integration of medical services—such as testing for infectious diseases,
treatments,
and management of chronic conditions—significantly improved access to healthcare, promoting
improvements in the
overall health of the drug-using population and increasing their adherence to
treatments30. This
strategy emerged as a key factor in improving quality of life and reducing
barriers to
accessing health services33.
Emotional and Motivational Support Interventions
These were aimed at strengthening treatment adherence and promoting behavioral changes related to
substance use. Early identification of at-risk students facilitated access to support networks
within the
school setting, making nursing professionals a key entry point for those seeking assistance27.
One of the main strategies was the Information-Motivation-Behavioral Skills (IMB) model, which
combines information provision with strategies to strengthen motivation and develop behavioral
skills
that reduce risky behaviors.
Nursing professionals played an essential role in guiding and referring patients to health services,
treatment programs, and social resources, promoting a holistic approach that integrates harm
reduction and comprehensive medical care30, based on the 5A model (ask, advise, assess, assist, and
arrange follow-up). They also involved families in the intervention process, strengthening the
support
network and creating a more favorable environment for recovery24.
Preventive Interventions
The studies focused on the early detection of substance use and the reduction of risk factors,
especially
among adolescents and students. Through screening programs and risk identification questionnaires,
nursing staff have been able to intervene promptly, preventing problematic patterns from evolving
into more serious disorders26,27. Their work in school settings through
educational programs and
informational talks, in collaboration with students, parents, and teachers, has been key to
promoting
healthy lifestyles, strengthening resilience to social pressure, and preventing the onset or
continuation
of drug use24. In
addition, the use of digital platforms has been promoted to facilitate informed
decisionmaking
and to reinforce general health promotion, including the prevention of communicable diseases
and opioid overdoses29.
Practical interventions for risk mitigation
Harm reduction interventions in the care of people who use drugs, both in hospital and community
settings, are essential strategies aimed at minimizing the risks associated with drug use without
requiring
abstinence. Among the most notable initiatives are sterile syringe exchange programs, which have
successfully reduced the transmission of infections such as HIV and hepatitis C, and the
distribution of
naloxone kits, empowering users and communities to respond to overdoses and effectively save
lives25,32.
Other relevant strategies include supervised consumption sites, where health professionals supervise
substance use under safe conditions, and the provision of safe injection kits in hospitals34,35.
These
measures not only reduce immediate risks such as overdose and infections but also facilitate access
to
health services and rehabilitation programs.
Discussion
The results of this study show that nursing interventions aimed at harm reduction for
people who use
drugs, developed within the PHC setting, focus on protecting life by strengthening access to health
services, as well as on reducing the transmission of HIV and hepatitis B and mortality from
overdose.
Furthermore, these interventions help protect the dignity of people who use drugs by promoting
respect for autonomy and non-stigmatization.
PHC represents individuals’ first point of contact with the healthcare system and
enables the creation
of ongoing therapeutic relationships with patients24,26. Barbara Starfield emphasizes that PHC is
characterized by providing person-centered, continuous, and coordinated care across different health
services—essential elements for adequately addressing the needs of vulnerable groups36.
From this perspective, the nursing team plays a fundamental role in implementing strategies such as
early
detection of substance use, health education, brief counseling, and ongoing follow-up with
individuals
who use drugs. Martínez Esquivel further emphasizes that nursing professionals who provide substance
use counseling must cultivate skills such as active listening, empathy, and assertive communication.
These qualities foster a therapeutic relationship based on respect and trust toward the user16.
These skills facilitate treatment through an approach that is not stigmatizing but rather
understanding,
which makes it easier to provide guidance on the risks associated with drug use and to promote safer
practices14,15. In general, these
proposals support the essential role of nursing in implementing
PHCbased
interventions that help reduce the risks and adverse effects associated with drug use, and improve
access to health services and the individual’s well-being15,16.
Among the interventions identified in the literature, health education stands out as one of the most
frequently implemented strategies in nursing care for people who use drugs. These actions include
providing information on the risks associated with drug use, early identification of signs of
overdose,
promotion of safer drug use practices, and guidance on timely access to health services. Together,
these
interventions contribute to increasing individuals’ knowledge, strengthening their capacity for
informed
decision-making, and reducing the adoption of risky behaviors, which promotes health protection and
the prevention of adverse events associated with drug use26.
Complementarily, the literature describes specific clinical interventions aimed at preventing
overdose
deaths, among which the distribution of naloxone accompanied by training in its use stands out. This
strategy is primarily implemented in contexts where opioid use constitutes a significant public
health
problem. Evidence shows that take-home naloxone programs are an effective measure for reducing
mortality by enabling an immediate response to potentially fatal events. In these programs, nurses
play
a fundamental role in educating, training, and monitoring users, which strengthens their ability to
act
promptly in emergencies related to substance use25.
Additionally, prevention interventions focused on strategies for access to supplies for safe
use—such
as needle exchange programs or the provision of sterile equipment—aim to reduce the transmission
of infections like HIV and viral hepatitis, among other complications related to injectable
substances.
These interventions seek to build trust among users in these settings and strengthen links with
other
health services33,37.
Similarly, the reviewed literature highlights the importance of interventions related to
accompaniment,
counseling, and psychosocial support, which are essential for comprehensively addressing the needs
of people who use drugs. These strategies promote adherence to treatment, facilitate access to
mental
health services, and help reduce the stigma associated with drug use—factors that, collectively, are
associated with improvements in quality of life and continuity of health care26,27.
A comparison of the analyzed studies shows that harm reduction interventions can be implemented
in various care settings—including hospitals, community-based settings, or specialized programs—
sharing the goal of reducing the negative consequences of drug use without necessarily requiring
abstinence. However, the scope and intensity of the interventions vary across studies, making it
difficult
to clearly establish which ones are most effective or offer the best cost-effectiveness for health
systems.
These differences reflect the diversity of approaches within the harm reduction model and highlight
the
need to adapt interventions to the specific characteristics of the context, available resources, and
the
particularities of the population served7,38,39.
Among the main limitations of this study is the limited availability of scientific literature on
nursing
interventions for harm reduction in the primary health care setting, especially in Latin American
contexts. This situation restricts the possibility of extrapolating the findings to health systems
and
sociocultural realities specific to the region. Additionally, it was found that many of the
available studies
analyze drug use in relation to various comorbidities, which can create methodological difficulties,
given that there is not always a direct causal relationship between these conditions and substance
use.
This interrelationship can hinder the precise identification of nursing interventions specifically
aimed at
harm reduction, introducing potential biases in the interpretation of the evidence.
The review did not include a systematic assessment of the methodological quality of the selected
studies, a factor that should be taken into account when interpreting the results. In addition, a
significant proportion of the studies analyzed (approximately 83%) originated in the United States
or
other developed countries, suggesting the need for cultural, organizational, and structural
adaptations
for their implementation in Latin American health systems.
Finally, based on the findings identified, it is recommended to strengthen recognition of the role
of
nursing professionals in the comprehensive care of people who use drugs, promoting greater levels of
professional autonomy in clinical decision-making based on scientific evidence. Similarly, it is
essential
that health policies incorporate strategies aimed at optimizing the use of available resources,
prioritizing
the prevention of adverse events and the reduction of complications associated with drug use. In
this
regard, it is necessary to promote new research that delves deeper into the effectiveness of nursing
interventions for harm reduction, particularly in Latin American contexts, to generate
contextualized
evidence that informs the design of more relevant and effective care policies and practices.
Conclusions
Through a comprehensive analysis of the literature, various interventions carried
out by nursing
professionals were identified, with education, counseling, emotional support, and clinical treatment
being the most prominent. However, specific harm reduction strategies, such as training and the
distribution of naloxone for overdose prevention, were less frequently reported in the analyzed
studies,
highlighting a gap in current research. Nevertheless, these strategies highlight the comprehensive
role of nursing, not only in the clinical management of addiction but also in risk prevention
through
educational and supportive interventions.
It was observed that educational and preventive interventions were the most frequent, particularly
among adolescents in school settings, helping to prevent the progression from experimental use to
abuse or drug dependence. Likewise, clinical interventions proved to be fundamental in improving
treatment adherence and reducing overdose mortality rates. Meanwhile, risk mitigation strategies
and emotional support promote users’ well-being and reduce harm associated with drug use. This
highlights the role of nursing staff in disciplinary competencies that enable them to lead
harmreduction
interventions, ensuring comprehensive care that addresses the biological, psychological,
and social dimensions of the individual.
Most of the included studies were conducted in the United States, which limits the transferability
of the results to other sociocultural and healthcare contexts. In this regard, it is recommended to
promote research in local contexts evaluating harm reduction strategies and nursing-led care models,
with the aim of generating contextualized evidence that contributes to strengthening public policies
and care programs in the region.
Conflict of Interest: The authors declare that they have no conflicts of interest.
Funding: This study is the result of the thesis titled “Nursing Interventions in
Primary Health Care
for
the Reduction of Harm Associated with Drug Use: A Scoping Review” from the Faculty of Nursing at
the Fundación Universitaria Sanitas and did not require funding.
Author Contributions: LMA-F: Conceptualization; Data Curation; Formal Analysis;
Investigation;
Visualization; Writing – Original Draft Preparation; Writing – Review & Editing. YLS-R:
Conceptualization;
Data Curation; Formal Analysis; Investigation; Visualization; Writing – Original Draft Preparation;
Writing – Review & Editing. FJC-M: Conceptualization; Investigation; Project Administration;
Supervision; Validation; Visualization; Writing – Review & Editing. JMS-R: Methodology;
Investigation;
Project Administration; Supervision; Validation; Writing – Original Draft Preparation; Writing –
Review
& Editing.
References
-
United Nations Office on Drugs and Crime.
World Drug Report: Key Messages. n.d. [Internet]
2023 [cited 2024 sept 3] Available from: https://www.unodc.org/res/WDR-2023/Special_Points_WDR2023_web_DP.pdf
-
Organización Mundial de la Salud (OMS).
Drogas y sustancias psicoactivas. Consulta:
Septiembre 3; 2024. Disponible en:
https://www.paho.org/es/temas/abuso-sustancias
-
Oficina de las Naciones Unidas contra la Droga y el Delito
(UNODC).
Estudio de consumo
de sustancias psicoactivas en Bogotá D.C. 2022. Consulta: Septiembre 3; 2024. Disponible
en: https://www.unodc.org/documents/colombia/2023/septiembre-9/ESTUDIO_DE_CONSUMO_DE_SUSTANCIAS_PSICOACTIVAS_BOGOTA_2022.pdf
-
Quimbita Cangui DD.
Factores Psicosociales Asociados al Consumo de Sustancias En Un Centro
de Rehabilitación. [Tesis de grado licenciatura en Psicología] Ambato; Ecuador; Universidad
Tecnológica Indoamérica;2023.
https://hdl.handle.net/20.500.14809/6028
-
Castro-Calle SJ; Orosco-Rosado DD; Murillo-Zavala AM; Carreño-Mera
GM.
Conductas
adictivas en adolescentes: prevalencia; factores de riego y complicaciones.
MQRInvestigar.
2023;7(3):3545–3560.
https://doi.org/10.56048/MQR20225.7.3.2023.3545-3560
-
Rodríguez M; Solari S; León L; Ramírez J; Pérez O; Guarda
E.
Complicaciones cardiovasculares
por uso de cocaína. Rev Chil Cardiol. 2007;26:459–466.
https://www.sscardio.org/wp-content/uploads/2008/rodriguez.pdf
-
Chasillacta FB; Núñez FR. Rol del personal de enfermería en
la atención primaria en salud. Salud;
Ciencia y Tecnología. 2022;2:82. https://doi.org/10.56294/saludcyt202282
-
Programa de las Naciones Unidas para el Desarrollo.
Objetivo 3: Salud y Bienestar; Objetivosde Desarrollo Sostenible. Consulta: Agosto 26; 2024.
Disponible en: https://www.undp.org/es/sustainable-development-goals/salud-bienestar
-
Colledge-Frisby S; Ottaviano S; Webb P; Grebely J; Wheeler A;
Cunningham EB; et al.
Global
coverage of interventions to prevent and manage drug-related harms among people who inject
drugs: a systematic review. Lancet Glob Health. 2023;11(5):e673–e683.
https://doi.org/10.1016/S2214-109X(23)00058-X
-
Wiessing L; Ferri M; Běláčková V; Carrieri P; Friedman SR; Folch C;
et al.
Monitoring quality
and coverage of harm reduction services for people who use drugs: a consensus study.
Harm
Reduct J. 2017;14:19.
https://doi.org/10.1186/s12954-017-0141-6
-
Magwood O; Salvalaggio G; Beder M; Kendall C; Kpade V; Daghmach W;
et al.
The
effectiveness of substance use interventions for homeless and vulnerably housed persons: A
systematic review of systematic reviews on supervised consumption facilities; managed
alcohol
programs; and pharmacological agents for opioid use disorder. PloS One.
2020;15(1):
e0227298.
https://doi.org/10.1371/journal.pone.0227298
-
Clua-García R.
La gestión de placeres y daños: Estudio etnográfico sobre el consumo de drogas
en vía pública; viviendas y salas de consumo higiénico. Salud Colect.
2020;16:65–66.
https://doi.org/10.18294/sc.2020.2481
-
Ondocsin J; Ciccarone D; Moran L; Outram S; Werb D; Thomas L; et al.
Insights from Drug
Checking Programs: Practicing Bootstrap Public Health Whilst Tailoring to Local Drug User
Needs.
Int J Environ Res Public Health. 2023;20(11):5999.
https://doi.org/10.3390/ijerph20115999
-
Romero Acosta DS.
Rol de Enfermería Frente a La Prevención; El Tratamiento y La
Rehabilitación Del Consumo de SPA. [Tesis de grado Enfermería]. Bogotá; Colombia;
Universidad
de Ciencias Aplicadas y Ambientales UDCA; 2018.
https://repository.udca.edu.co/entities/publication/66926bce-016c-41a5-b7d3-13bf5adf2ae6
-
López Alabarce JA; Hernández Sánchez D; Molina Mula J; Fernández
Medina JM; Castaño
Fernández AI; Sanz Álvarez E; et al.
Percepción; conocimientos y actitudes de las enfermeras
de urgencias y salud mental frente al alcoholismo y otras drogodependencias. Metas
Enferm.
2014;17(2):22-31.
https://www.enfermeria21.com/revistas/metas/articulo/80555/
-
Martínez Esquivel D.
Cualidades del personal de enfermería en salud mental para las consejerías
en adicción a drogas. Enferm Actual de Costa Rica. 2019;(37):223–233. https://www.scielo.sa.cr/scielo.php?script=sci_arttext&pid=S1409-45682019000200223
-
Organización Panamericana de la Salud (OPS).
Atención Primaria de Salud. Consulta:
Septiembre 3; 2024. Disponible en: https://www.paho.org/es/temas/atencion-primaria-salud
-
Starfield B.
Atención Primaria: Equilibro Entre Necesidades de Salud; Servicios y Tecnología.
Masson: Nueva York; NY; Estados Unidos de América: Oxford University Press; 1998.
-
Levac D; Colquhoun H; O’Brien KK.
Scoping studies: advancing methodology. Implement Sci.
2010;5:69. https://doi.org/10.1186/1748-5908-5-69
-
Ouzzani M; Hammady H; Fedorowicz Z; Elmagarmid A. Rayyan — a web and
mobile app for
systematic reviews. Systematic Reviews. 2016;5:210;
https://doi.org/10.1186/s13643-016-0384-4
-
Tricco AC; Lillie E; Zarin W; O'Brien KK; Colquhoun H; Levac D; et
al.
PRISMA extension for
scoping reviews (PRISMA-ScR): checklist and explanation. Ann Intern Med. 2018;
169(7):467-473.
https://doi.org/10.7326/M18-0850
-
Sánchez-Rodríguez JM; Acuña-Forero LM; Sosa-Rodríguez YL;
Cárdenas-Martínez FJ.
Intervenciones de enfermería en Atención Primaria en Salud para la reducción de daños
asociados al consumo de drogas: Scoping review. Figshare. 2025
https://doi.org/10.6084/m9.figshare.29371472
-
Ministerio de Salud - República de Colombia. Resolución 8430 de
1993. Por la cual se
establecen las normas científicas; técnicas y administrativas.
Resolución 8430 de 1993. Por la cual se
establecen las normas científicas; técnicas y administrativas para la investigación en
salud.
Consulta: Septiembre 3; 2024.
-
Gutierrez A; Sher L.
Alcohol and drug use among adolescents: an educational overview. Int J
Adolesc Med Health. 2015;27(2):207–12;
https://doi.org/10.1515/ijamh-2015-5013
-
World Health Organization.
Management of common health problems of drug users. Regional
Office for South-East Asia. [Internet] 2008 [cited 2008 April 8]. https://iris.who.int/bitstreams/e97ba910-52a7-4527-8fd7-2c91fe405d22/download
-
Pengpid S; Peltzer K; Van der Heever H; Skaal L.
Screening and brief interventions for hazardous
and harmful alcohol use among university students in South Africa: results from a randomized
controlled trial. Int J Environ Res Public Health. 2013;10(5):2043–57.
https://doi.org/10.3390/ijerph10052043
-
Patestos C; Patterson K; Fitzsimons V.
Substance abuse prevention: the role of the
school nurse across the continuum of care. NASN Sch Nurse. 2014;29(6):310–4. https://doi.org/10.1177/1942602x14542655
-
Lintzeris N; Monds LA; Bravo M; Read P; Harrod ME; Gilliver R; et al.
Designing; implementing
and evaluating the overdose response with take-home naloxone model of care: An evaluation of
client outcomes and perspectives. Drug Alcohol Rev. 2020;39(1):55–65. https://doi.org/10.1111/dar.13015
-
Morales Loyola M.
Iniciativa educativa e-Salud con enfoque en reducción de riesgos y daños del
consumo de sustancias psicoactivas en adolescentes escolarizados del Estado de México.
[Tesis
de posgrado] Escuela de Salud Pública de México: Cuernavaca; Morelos; 2022.
-
Burr CK; Storm DS; Hoyt MJ; Dutton L; Berezny L; Allread V; et al.
Integrating health and
prevention services in syringe access programs: a strategy to address unmet needs in a
high-risk
population. Public Health Rep. 2014;129:26–32. https://doi.org/10.1177/00333549141291s105
-
Cataldo JK.
The role of advanced practice psychiatric nurses in treating tobacco use and
dependence. Arch Psychiatr Nurs. 2001;15(3):107–19. https://doi.org/10.1053/apnu.2001.23749
-
Sharma M; Lamba W; Cauderella A; Guimond TH; Bayoumi AM.
Harm reduction in hospitals.
Harm Reduct J. 2017;14. https://doi.org/10.1186/s12954-017-0163-0
-
Perera R; Stephan L; Appa A; Giuliano R; Hoffman R; Lum P; et al.
Meeting people where
they are: implementing hospital-based substance use harm reduction. Harm Reduct J.
2022;19.
https://doi.org/10.1186/s12954-022-00594-9
-
Mullennix SC; Iseler J; Kwiatkowski GM; McCann-Spry L; Skinner J; Kuhl N; et
al.
A Clinical
Nurse Specialist-Led Emergency Department Naloxone Distribution Program. Clin Nurse
Spec
CNS. 2020;34(3):116–123; https://doi.org/10.1097/NUR.0000000000000515
-
Clua-García R.
Cuidados de Enfermería y Promoción de La Salud En Las Salas de Consumo
Higiénico. Cultura De Los Cuidados. 2021;25(60):193-211. https://culturacuidados.ua.es/article/view/2021-n60-Cuidados-de-enfermer%C3%ADa-y-promoci%C3%B3n-de-la-salud-en-las
-
Smith J.
Primary care: balancing health needs; services and technology. Int J Integr Care.
2001;1:e36. https://pmc.ncbi.nlm.nih.gov/articles/PMC1484414/
-
Harm Reduction International.
¿Qué es Reducción de Daños? Consulta: Septiembre 3; 2024.
Disponible en: https://hri.global/what-is-harm-reduction/spanish/
-
Ramos Calero E.
Enfermería Comunitaria Métodos y Técnicas. 2a. ed. La Enfermería Viva.
Enfermería 21. Difusión Avances de Enfermería: Madrid; 2002.
-
Sánchez Hervás E; Tomás Gradolí V; del Olmo Gurrea R; Molina Bou N; Morales Gallús
E.
Terapia cognitivo-conductual breve en un grupo de dependientes a drogas. Revista de
la Asociación Española de Neuropsiquiatría. 2002;(81):21–29. https://scielo.isciii.es/scielo.php?script=sci_arttext&pid=S0211-57352002000100003
Supplementary Material 1. Categories described according to
interventions
X
Supplementary Material 1. Categories described according to interventions
| Category |
Intervention |
Description |
Educational /
psychoeducational
|
Education on the risks and
benefits of quitting smoking.
|
Intervention known as the 5Rs: relevance; where it is
explored whether quitting smoking is
personally relevant; risks; where the patient is helped
to identify the negative consequences
of tobacco use; rewards; where the benefits of quitting
tobacco use are identified; roadblocks;
where the patient’s barriers or impediments to quitting
smoking are identified; and repetition;
where it is clarified that this intervention must be
repeated in each treatment session; these are
most successful when staff are empathetic; promote
autonomy; and support the patient’s selfefficacy31
.
|
|
Education on the prevention
of infectious diseases.
|
Advise all couples on the consistent use of condoms and
emphasize adherence to treatment. If
arterial or skin lesions such as abscesses; swelling; or
severe inflammation are observed; seek
medical attention. When injecting drugs; ensure good
skin hygiene and handwashing; along
with the use of clean injection equipment each time; and
recommend reducing the frequency
of injections25
.
|
|
Brief intervention to
discuss strategies for
reducing excessive alcohol
consumption.
|
After administering the AUDIT questionnaire; provide
personalized feedback on the results;
offer a health education pamphlet with simple tips; and
provide brief counseling on how to
reduce excessive alcohol consumption during a 20-minute
session over a 3-month period26
.
|
|
Education on safe injection
practices and overdose
prevention.
|
The New Jersey Department of Health contracted a
resource center to train nurses on patient
care; implementing an orientation program and bimonthly
meetings. Nurses received support
to identify local resources and establish standing
orders for nursing interventions; so they
began offering health promotion services; including
wound care; counseling on safer injection
techniques and overdose prevention; and counseling on
safe sex and reproduction30
.
|
|
Educational programs in
schools on the risks of drug
use.
|
School districts should allocate funds to effective
educational programs for identifying the
risks of drug use; the nurse’s role is to evaluate
prevention programs from an evidence-based
perspective; make recommendations to administrators;
students; families; school staff; and the
community; as well as implement these programs to reduce
drug use27
.
|
|
Education on the harmful
effects of alcohol and drug
use.
|
Workshops and educational sessions were conducted for
adolescents; informing them about
the physical; psychological; and social risks associated
with alcohol and other drug use.
This education also addressed the impact of substance
use on brain development; academic
performance; and interpersonal relationships24
.
|
|
Education on how to identify
signs of overdose.
|
Brief intervention (10–30 minutes) with individual
participants; which included education
on opioid overdose prevention and response; as well as
safe use of naloxone. The education
consisted of assessing patients’ knowledge of the risk
factors for an opioid overdose; how to
identify and respond in the event of a suspected
overdose; and their knowledge and experience
with naloxone. Additionally; concerns and questions
regarding the risks and responses to an
overdose were addressed; the patient was educated on the
use of naloxone to take home; and a
consumer information sheet was provided; with a
follow-up conducted at 3 months28
.
|
|
Training for patients and
family members on the
administration of naloxone.
|
A 3-minute educational video on naloxone was developed;
presenting a realistic scenario that
reviewed the signs and symptoms of an opioid overdose
and demonstrated how to respond
immediately to the situation using a commercially
available naloxone nasal spray34
.
|
|
Education on the risks of
substance use through digital
platforms.
|
Through the e-Health approach; digital platforms were
used to present information on harm
reduction and substance use-related risks; the skills
promoted included decision-making; selfefficacy;
and resistance to peer pressure29
.
|
Clinical
interventions
|
Pharmacological treatment
for smoking cessation.
|
Nicotine users attempting to quit smoking should receive
pharmacotherapy with first-line
medications; which include nicotine replacement
therapies—such as patches; gum; sprays; and
inhalers—that are tapered off as the patient tolerates
them without causing withdrawal; and
sustained-release bupropion; which should be
administered for 8 to 12 weeks with a minimum
maintenance period of 6 months31
.
|
Medical treatment for
infections and common
illnesses among drug users.
Vaccination against hepatitis
and tetanus.
|
Management of sexually transmitted infections with
antibiotics or antivirals and management
of skin lesions with antibiotics and analgesics for
pain; or; if necessary; incision and drainage.
For tetanus vaccination; 0.5 ml of tetanus toxoid should
be administered intramuscularly in the
upper arm after the skin is cleaned with an alcohol
swab. Notify the patient when the next dose
is due; as there are 5 doses (1 month; 6 months; 1 year;
and 1 year). For hepatitis B; the dose of
Engerix-B and Recombivax HB is 0.5 mL IM up to age 20 or
1 mL IM for adults (≥ 20 years).
The dose of Heplisav-B (HepB-CpG) is 0.5 mL IM for
adults ≥ 18 years of age; administered in
3 doses. The second dose is administered 1 month after
the first dose; followed by a third dose
6 months after the second25
.
|
|
Access to medical care and
HIV/hepatitis testing.
|
DAs part of the needle exchange program; participants
also had access to basic care to reduce
barriers to care and receive comprehensive care;
therefore; HIV and hepatitis testing were
conducted to facilitate early diagnosis and treatment in
the event of positive results; ensuring
pre- and post-test counseling30
.
|
|
Treatment of drug-related
infections.
|
Injecting drug users who come to the hospital for
infections and require prolonged treatment
can be managed with antibiotics; preferably administered
via intravenous catheters; as evidence
for the efficacy of oral antibiotics is weak; however;
caution must be exercised regarding primary
infections associated with the intravenous
catheter32
.
|
|
Provision of medical care to
people with substance use
disorder.
|
People with substance use disorder should receive
medical care at various harm reduction sites;
where each patient’s needs are taken into account;
providing personalized care that includes
support services; diagnostic testing and treatment for
hepatitis C and HIV; overdose prevention;
naloxone; condoms; and referrals to addiction
services33
.
|
Emotional and
motivational support
interventions.
|
|
Ongoing follow-up and
emotional support for
patients.
|
Ongoing follow-up and emotional support for patients.
The “5A” intervention; in
which tobacco users are identified and asked about their
use; smokers are then advised to
quit; as this benefits their health; the patient’s
willingness to attempt to quit is subsequently
assessed; the patient is helped to quit through
practical advice and social support; and finally;
a follow-up program is organized; either in person or by
telephone31
.
|
|
Individualized counseling to
quit smoking.
|
Three components must be taken into account: practical
counseling; social support within
treatment; and social support outside of treatment.
Practical counseling focuses on problemsolving;
encouraging recognition of high-risk situations and the
development of coping skills;
within social support in treatment; the patient is
encouraged to discuss the process of quitting
smoking; express concern; and demonstrate a willingness
to help31
.
|
|
Information-Motivation-
Behavioral Skills (IMB)
Model.
|
In this intervention; in addition to providing
information on methods for reducing and
preventing harmful use; it is necessary to generate
motivation to change behavior and foster
behavioral skills that alter risky consumption patterns;
which is crucial for harm reduction26
.
|
|
Connecting students with
counseling or treatment
services.
|
In the school setting; the school nurse serves as the
link between the student; their family;
and the community and health services; particularly when
providing drug abuse prevention
programs27
.
|
|
Behavioral and family
therapies.
|
Cognitive-behavioral therapies are conducted with the
aim of teaching adolescents coping
skills they can use when facing situations and feelings
that trigger a return to alcohol or drug
use. Additionally; interventions were conducted with
family members to identify behavioral
and communication patterns that might be related to
substance use; including conflict
resolution skills and the promotion of a supportive
family environment24
.
|
|
Connection to health services
and treatment for drug users.
|
Within supervised consumption sites; interventions are
not only aimed at supervising
consumption but also at helping patients access
additional health services such as addiction
treatment; mental health counseling; and rehabilitation
programs; thereby addressing not
only the physical but also the emotional and social
needs of the user35
.
|
|
Preventive
interventions
|
|
Education on the prevention of
infectious diseases.
|
Providing STI counseling and testing. Drop-in centers
have been shown to have a positive impact
on increasing knowledge among the drug-using population
regarding HIV/AIDS prevention;
overdose prevention; and other health issues25
.
|
|
Screening to identify
problematic alcohol use.
|
The Alcohol Use Disorders Identification Test (AUDIT)
should be administered; it consists of 10
items assessing levels of alcohol consumption (three
items); symptoms of alcohol dependence
(three items); and problems associated with alcohol
consumption (four items); for a maximum
score of 40. Individuals scoring 8 or higher are
identified as at-risk drinkers or those with a
tendency toward problematic drinking and should
therefore receive educational intervention26
.
|
|
Early detection of substance
abuse problems.
|
Drug abuse screening should begin at school age;
therefore; both risk factors and protective
factors for drug abuse must be identified; addressed;
and influenced within the contexts of the
individual; family; community; and society27
.
|
|
Prevention of substance
use initiation through
informational talks.
|
Selective interventions focus on high-risk adolescents;
while targeted interventions focus on
those who already use substances. Their goal is to
reduce substance use and prevent progression.
Additionally; early recognition and treatment of mood
disorders can prevent substance use; and
limiting access to alcohol and other drugs is essential
for prevention; since substance use at home
is one of the main factors that lead adolescents to want
to start using them24
.
|
|
Distribution of naloxone
and training on its use to
prevent overdose-related
complications.
|
Providing clients with naloxone to take home. The
project used a pre-filled syringe for
intramuscular injection (2 ml containing 5 mg/ml). X 0.4
mg dose). This medication was provided
free of charge to the user28
.
|
|
CScreening patients at risk of
opioid overdose.
|
Risk factors for opioid overdose should be identified in
individuals presenting to emergency
departments. This involves determining whether the
patient has any of the following: a history
of overdose; a history of substance use disorder; a
mental health condition; participation in a
detoxification program; use of high doses of opioids; or
a prescription for opioid medication34
.
|
|
Prevention of problematic
substance use among
adolescents through accessible
information.
|
Central to the approach of e-health interventions is the
harm reduction model; whose
interventions promote virtual environments as an
alternative that brings health services closer
to people; with the aim of keeping people alive and
motivating them to make positive changes in
their lives; preventing experimental use and sporadic
use from becoming chronic use; reducing or
limiting the harm caused to the health of people who use
drugs; and decreasing the undesirable
socio-health effects associated with their use29
.
|
|
Practical
interventions for risk
mitigation
|
|
Provision of clean needles and
sterile injection equipments.
|
Strategies for distributing clean needles and sterile
injection equipment were implemented
to promote safe injection practices. Additionally;
information was provided on the safe use of
injectable medications; including not reusing or sharing
needles to prevent infections and the
spread of communicable diseases; rotating injection
sites; etc25
.
|
|
Provision of clean syringes and
safe injection equipment.
|
Syringe access programs were implemented in five cities
in New Jersey. The program consisted of
distributing sterile syringes and other injection
equipment; such as alcohol swabs; sterile water;
and filters; this prevented the sharing of these items;
with the aim of promoting safe injection
practices and reducing the transmission of infectious
diseases30
.
|
|
Provision of sterile materials
(syringes) for people who use
drugs.
|
Needle and syringe programs focus on the distribution of
syringes; needle exchange; and the
provision of sterile equipment for people who use drugs;
it is also important that injection kits
be provided during healthcare visits to mitigate the
risk of contracting bloodborne infections32
.
|
|
Distribution of naloxone in the
emergency department.
|
Naloxone should be distributed to adults and adolescents
who received care in the emergency
department following an opioid overdose; providing a
naloxone kit to take home and establishing
a standard of care and evidence-based clinical
guidelines that include recommendations for the
distribution of a commercially prepared 4 mg intranasal
naloxone spray; to be prepared for future
out-of-hospital overdoses34
.
|
|
SPost-discharge follow-up
to ensure access to care and
treatment resources.
|
Patients who received education through the educational
video and were provided with naloxone
kits were given access to the video at any time after
discharge via a QR code to ensure quick access;
it is also important to follow up with individuals who
received the kit through medical visits34
.
|
|
Supervision and care in
supervised consumption sites.
|
Nurses follow established protocols to supervise drug
users who visit supervised consumption
sites (SCSs) to ensure consumption takes place under
hygienic and safe conditions; with the goal
of improving injection technique and reducing the
incidence of abscesses. Patients learn to space
out their drug use; thereby reducing the risk of
overdose. Workshops on hygienic venipuncture
are conducted; protocols are used to monitor vital signs
and administer medications; and
cardiopulmonary resuscitation techniques are employed.
Additionally; nursing care and health
promotion interventions are provided for skin and foot
injuries; as well as other conditions related
to users’ lifestyles35
.
|
|
Implementation of harm
reduction programs in
hospitals.
|
Harm reduction programs were implemented; which are
based on providing supplies and
education depending on the drug and route of use:
For alcohol; a brochure titled “Rethinking Alcohol
Consumption” is provided; which offers
advice on safe drinking; such as reducing the number of
days consumed; eating before drinking;
alternating with water; etc. For tobacco; education is
provided; along with toothpicks and gum to
reduce the “craving” to smoke. For opioids or stimulants
consumed by smoking or inhalation; a
Pyrex pipe and rubber mouthpiece are provided; along
with education to reduce the need to reuse
and share equipment; thereby lowering the risk of
infection; for injected opioids or stimulants; in
addition to education on overdose prevention; injection
kits are provided that contain a needle;
tourniquet; alcohol wipes; a sharps container; naloxone;
and condoms33
.
|
✖

Figura 1. Título de la figura.